Case studyPrescriberPointHealthcare
Designing for the clinic staff who get prescriptions through
PrescriberPoint set out to make medication access easier for the people who prescribe and the clinic staff who carry prescriptions through insurance, funded by the pharmaceutical manufacturers who want those prescriptions filled. As head of product design and research, I built an in-house practice, made clinic staff the primary user, led a rebrand and a utility-first homepage, and wrote the context scenario behind OneHub’s prior authorization automation. As interim product lead for Marketplace, I made the case for turning traffic into an audience that came back.
- Company
- PrescriberPoint, a medication access platform born out of BCG
- My role
- Head of Product Design & Research; later also interim product lead, Marketplace
- When
- 2024 to 2026
- Team
- Two product designers, a content designer, and two UX researchers
- Reported to
- Chief Technology Officer
Results
What I led
- Launcheda new brand and a utility-first homepage across the site, September 2025
- 5designers and researchers in an in-house practice, where an agency had led design
- 0 → 1the interaction model behind OneHub’s automated prior authorization, from my context scenario
No post-launch metrics to report.
The company
Getting a patient onto the right medication is often harder than deciding what to prescribe. Insurance requirements, prior authorizations, manufacturer programs, and savings options are scattered across systems that don’t talk to each other, and the work falls on clinics.
PrescriberPoint had two products. Marketplace was the public site, with the information people needed to get a patient onto therapy. OneHub was a SaaS platform to automate prior authorization itself, built to compete with CoverMyMeds, the established tool in the industry. Pharmaceutical manufacturers paid for what both could deliver: more prescriptions written, approved, and filled.
The system
A prescription passes through several hands before it reaches the pharmacy, and any of them can send it back:
- PrescriberDiagnoses the patient and writes the prescription
- Clinic staffCheck coverage, submit prior authorization, and find savings
- InsurerApproves, asks for more, or rejects the request
- PharmacyFills the prescription, and the patient starts therapy
Each part of the system carried its own constraint:
- Two customers, one businessCare teams needed the product to be useful; manufacturers paid for it to change outcomes
- Information alone wasn’t enoughA page about a drug doesn’t help someone whose prior authorization was just rejected
- Staff work in other systemsStaff work inside electronic health records and payer portals, not on another website
- Clinics adopt, not individualsChanging a workflow tool takes operations, IT, and procurement, even when the tool is free
- A brand that didn’t exist yetThe site pitched a SaaS company more than it helped anyone do their work
- Pressure to use AIPressure to use generative AI everywhere, before anyone knew where it helped
What I did
The company was named for prescribers, and manufacturers saw prescribers as the way to get more prescriptions filled. My strategy was to design for the clinic staff who get prescriptions through, and to give them tools they would come back to, so that trust in PrescriberPoint could lead clinics to adopt OneHub.
In practice, that meant:
- Find who does the work. Put researchers in clinics, and let what they saw set the primary user.
- Rebuild the brand around access. Position the company around access to medication, not software.
- Design the path from visitor to customer. Map how trust in the site could grow into a clinic adopting OneHub, and make the case for building it.
- Redesign the homepage around jobs to be done. Lead with the tasks people came to do.
- Define OneHub through a context scenario. Describe how people are supported before specifying features.
- Build the practice, and set the terms for AI. Hire in-house, and give teams principles for working with generative AI.
I inherited a junior researcher, two product designers in Latin America, and an agency that had been leading design. Over the next year I hired a content designer and two UX researchers, one senior, and partnered with Tina Ivankovic, our director of marketing design, so product and marketing worked from one design language. Later, I also took interim responsibility for the Marketplace product, without product managers under me, while still leading design and research.
Track one
Defining the product
From research in clinics to a new brand, a path from visitor to customer, a homepage built on jobs to be done, and the context scenario behind OneHub.
Find who does the work
I put one researcher on Marketplace and one on the clinic side, where OneHub would live. We went into clinics, interviewed staff, and watched them work, from the moment a prescription was written to the moment it reached the pharmacy, and mapped what we saw as a service blueprint.
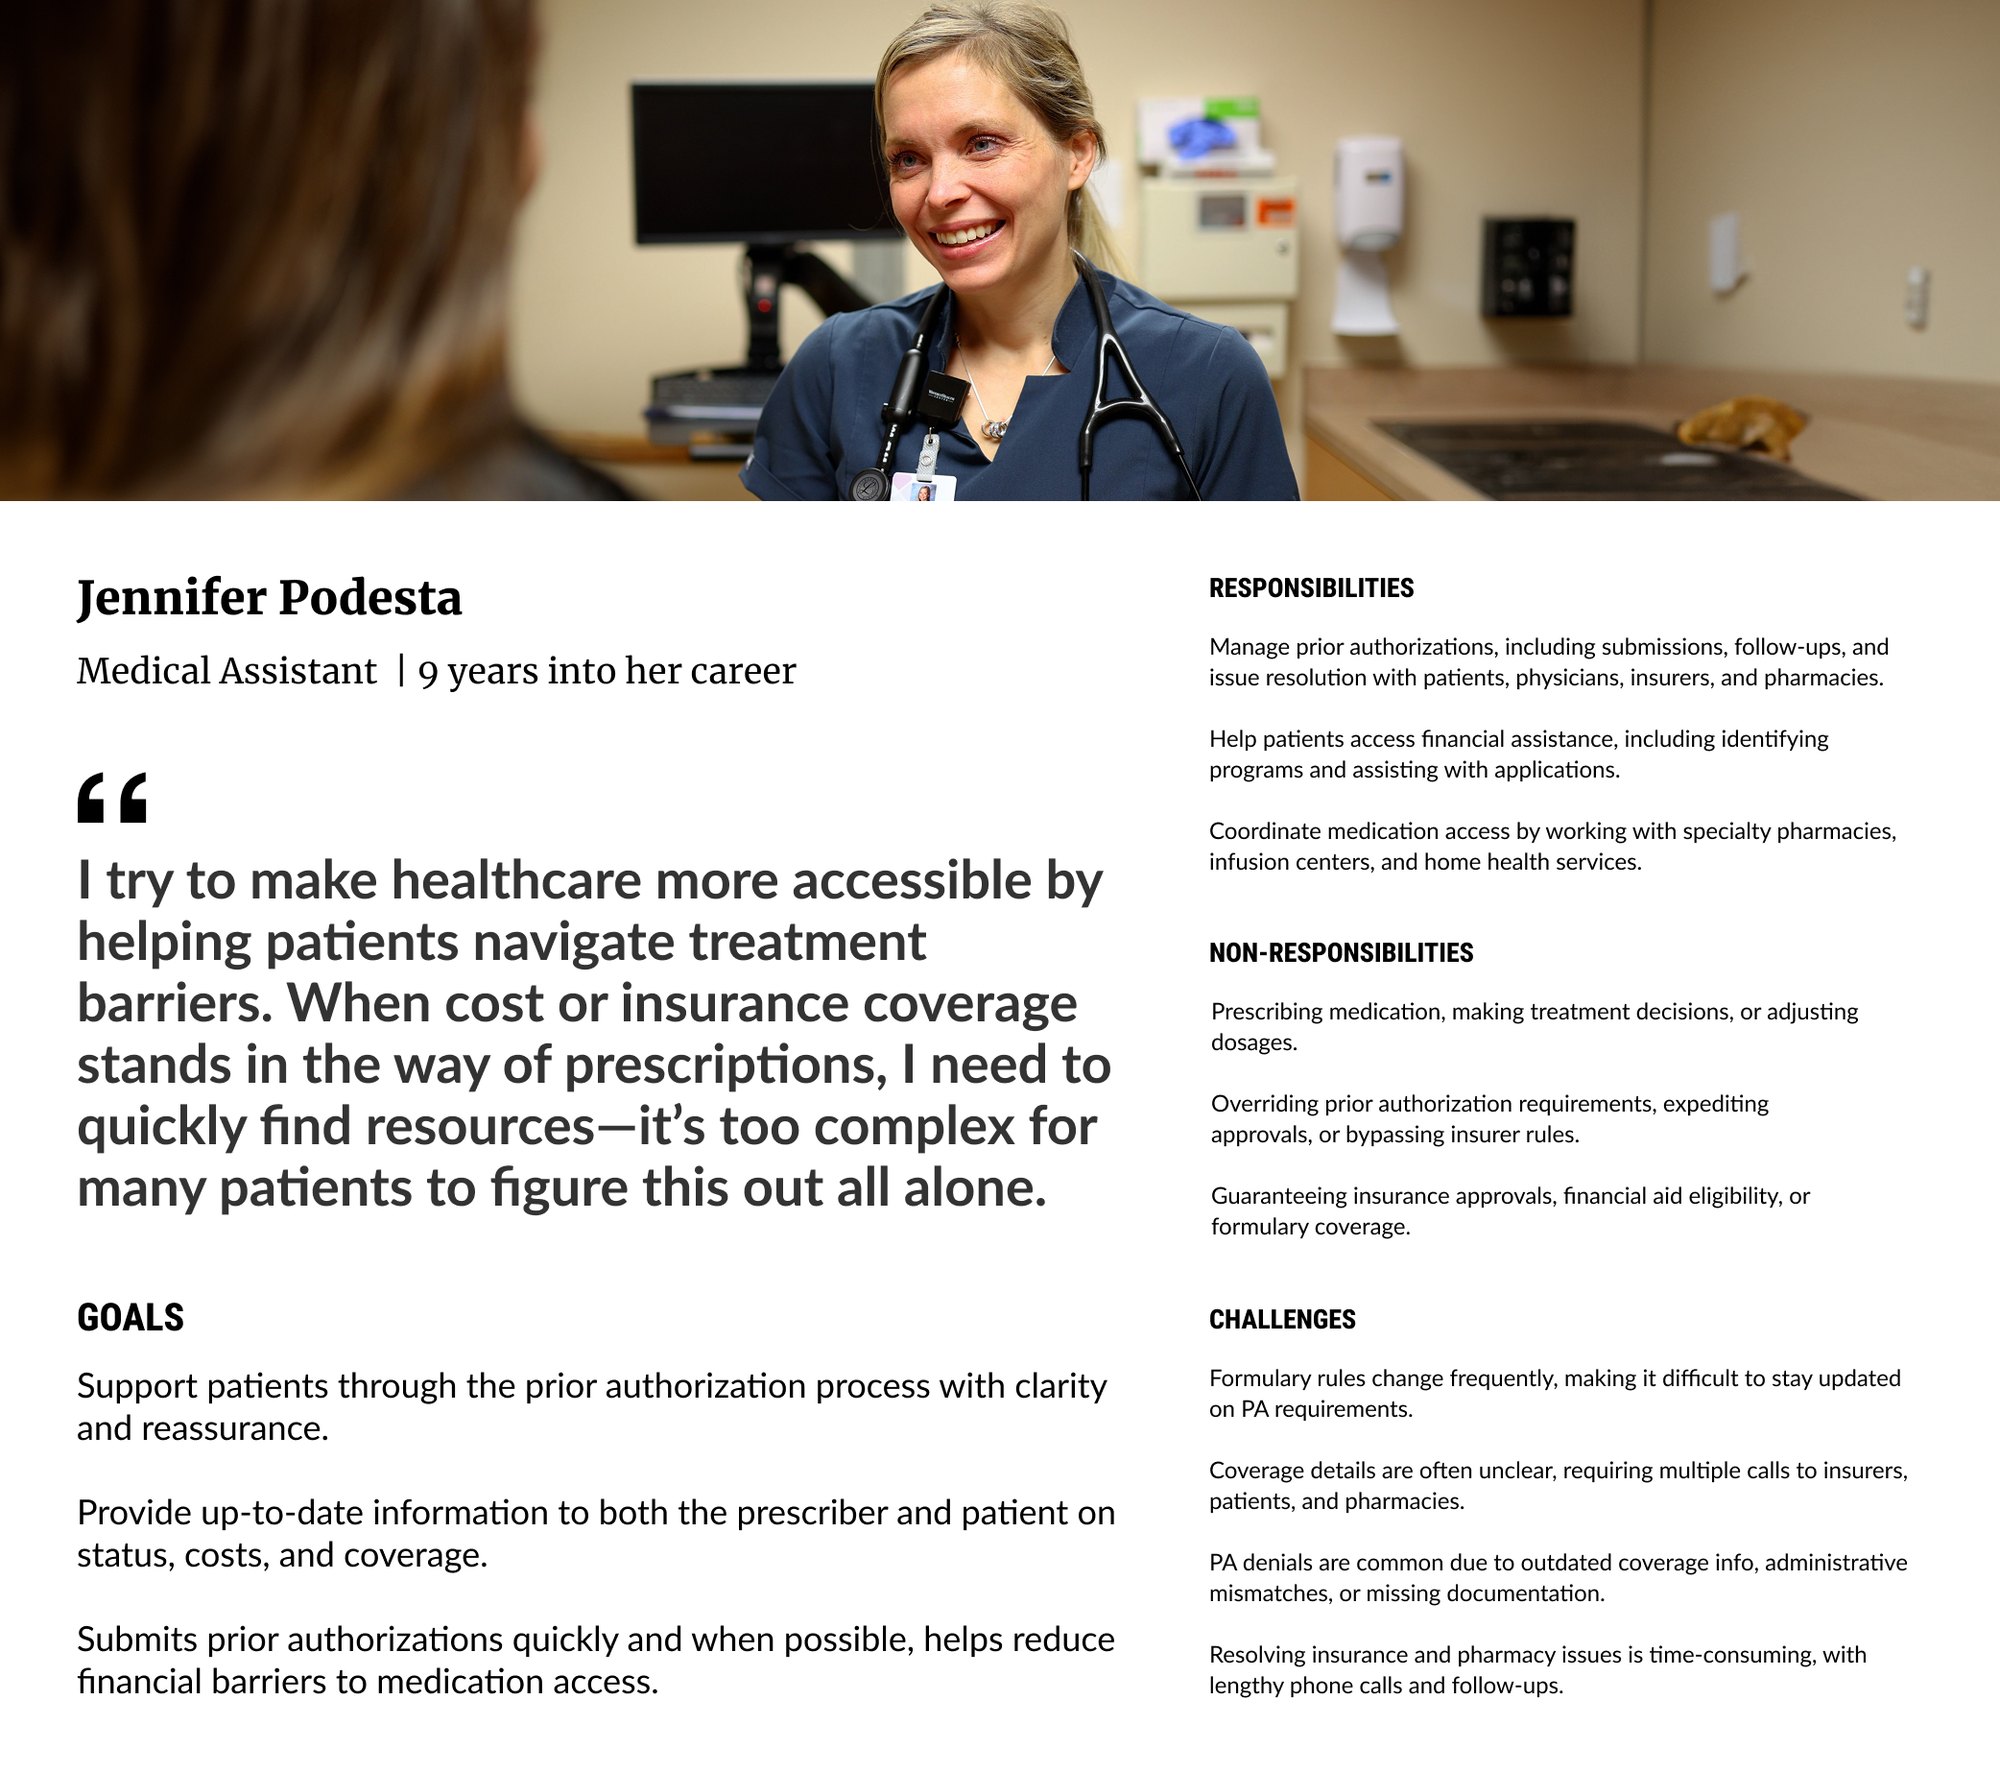
What we found changed who we designed for. Prescribers write prescriptions, but clinic staff get them through, and a prescription can stall for many reasons. Their jobs went well beyond prior authorization: comparing medications, finding a savings program when a patient couldn’t afford a drug, and switching to a second option when an insurer’s requirements were too heavy. Clinic staff became our primary persona. Prescribers mattered too, but we served most of them through samples, a smaller part of the business.
| Phase | Prescription | Prior authorization | Fill | Renewal | |||||
|---|---|---|---|---|---|---|---|---|---|
| Lane | Consultation | Prescription sent | Check the case | Submit | Decision | Resubmit | Appeal | Dispense | Renewal |
| Patient | Visits the doctor and gets a diagnosis | Told a prescription went to the pharmacy | Confirms personal and insurance details | Waits, and asks for updates | Waits | — | Pushes for an appeal | Hears it’s approved, and picks it up | Pushes for a renewal |
| Clinic staff, with the patient | Prescriber decides a medication is needed | Pharmacy rejects it for a missing prior authorization | Staff chase missing clinical and patient information | Staff tell the patient the request has started | Staff hear back from the insurer | — | — | Staff tell the patient | — |
| Behind the scenes | — | Pharmacy checks eligibility | Staff gather records and call the insurer | Staff complete and submit the request with documentation, and track its dates | Approval or denial arrives | Staff resubmit with more evidence, sometimes more than once | Staff appeal on the patient’s behalf; few cases qualify | Pharmacy verifies the authorization | Staff track expirations and resubmit before coverage lapses |
| Tools | In person | E-prescribing | Phone, messages, video | Spreadsheets, fax, phone | — | Phone | Phone | Fax | Phone |
| Burden on staff | Light | Light | Heavy | Heavy | Moderate | Heaviest | Heaviest | Light | Heavy |

Rebuild the brand around access
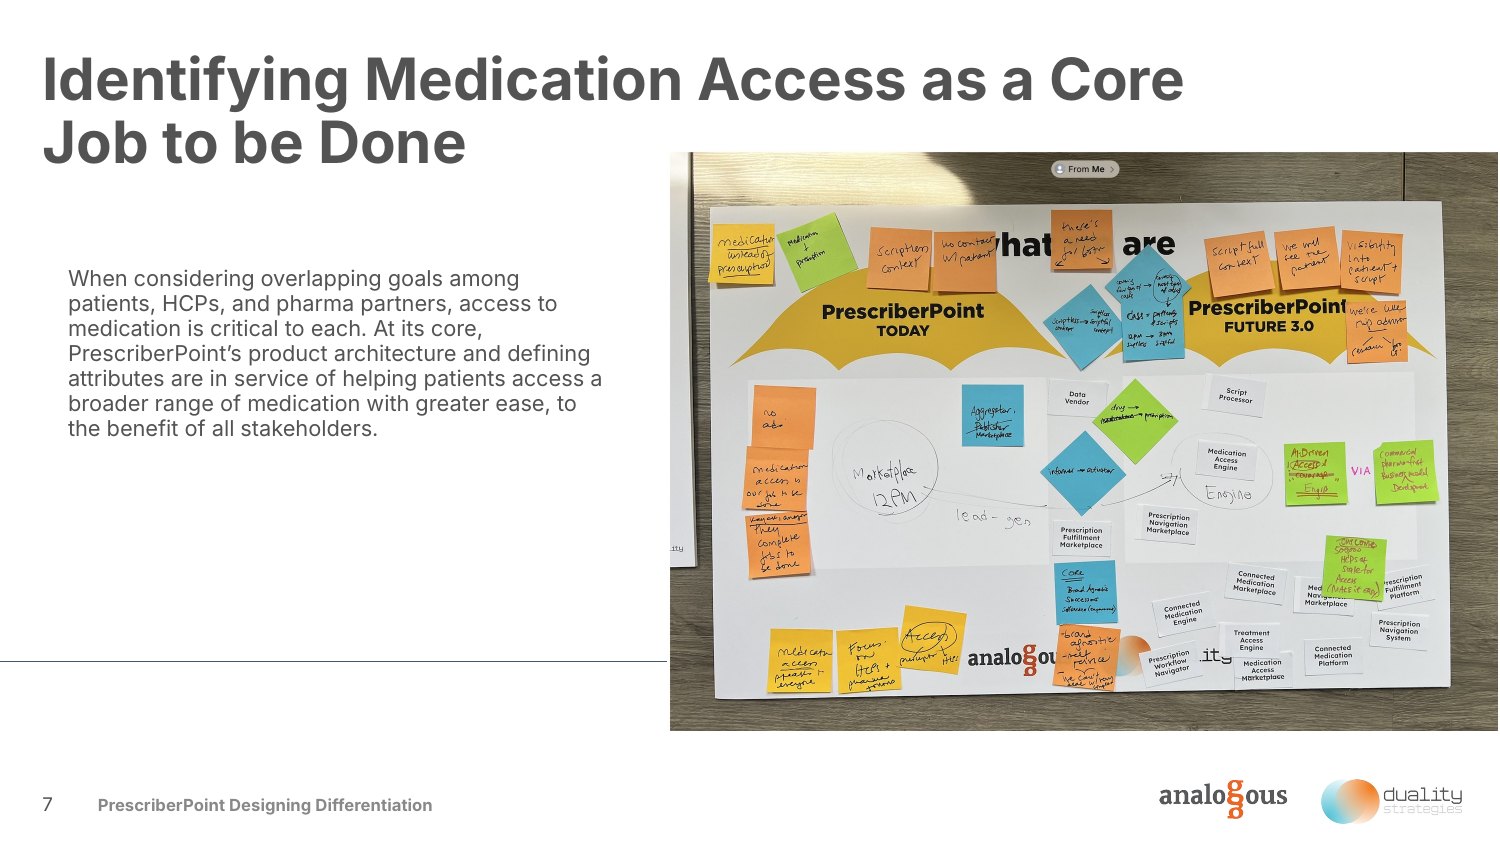
PrescriberPoint didn’t have an established brand, and its site read like a SaaS pitch. In March 2025, I brought in Studio Analogous for a brand strategy engagement. They interviewed the entire executive team and other key players, and a few months later we ran a workshop with the whole team in Boston.
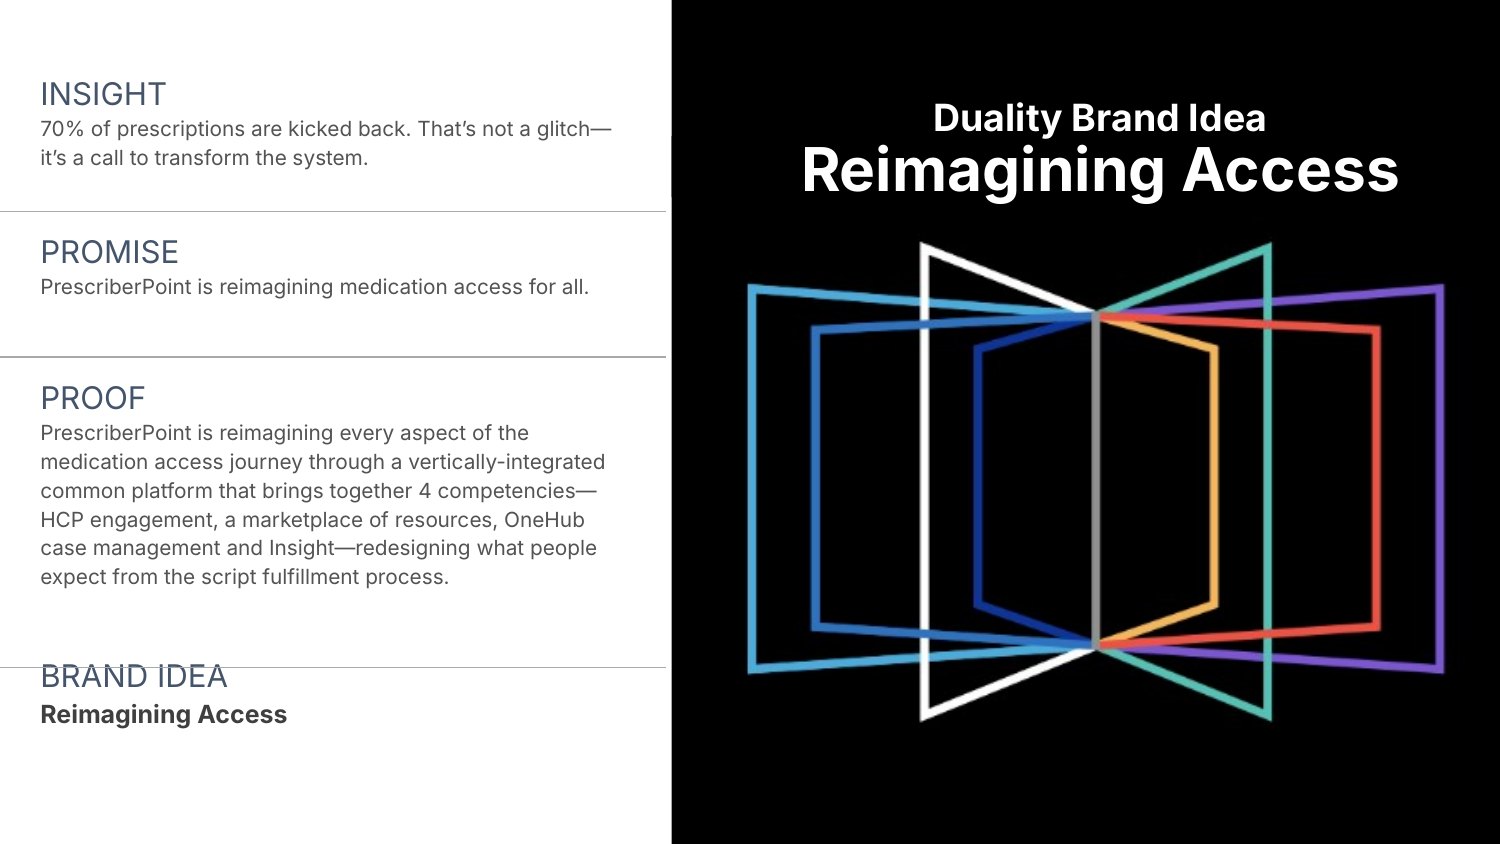
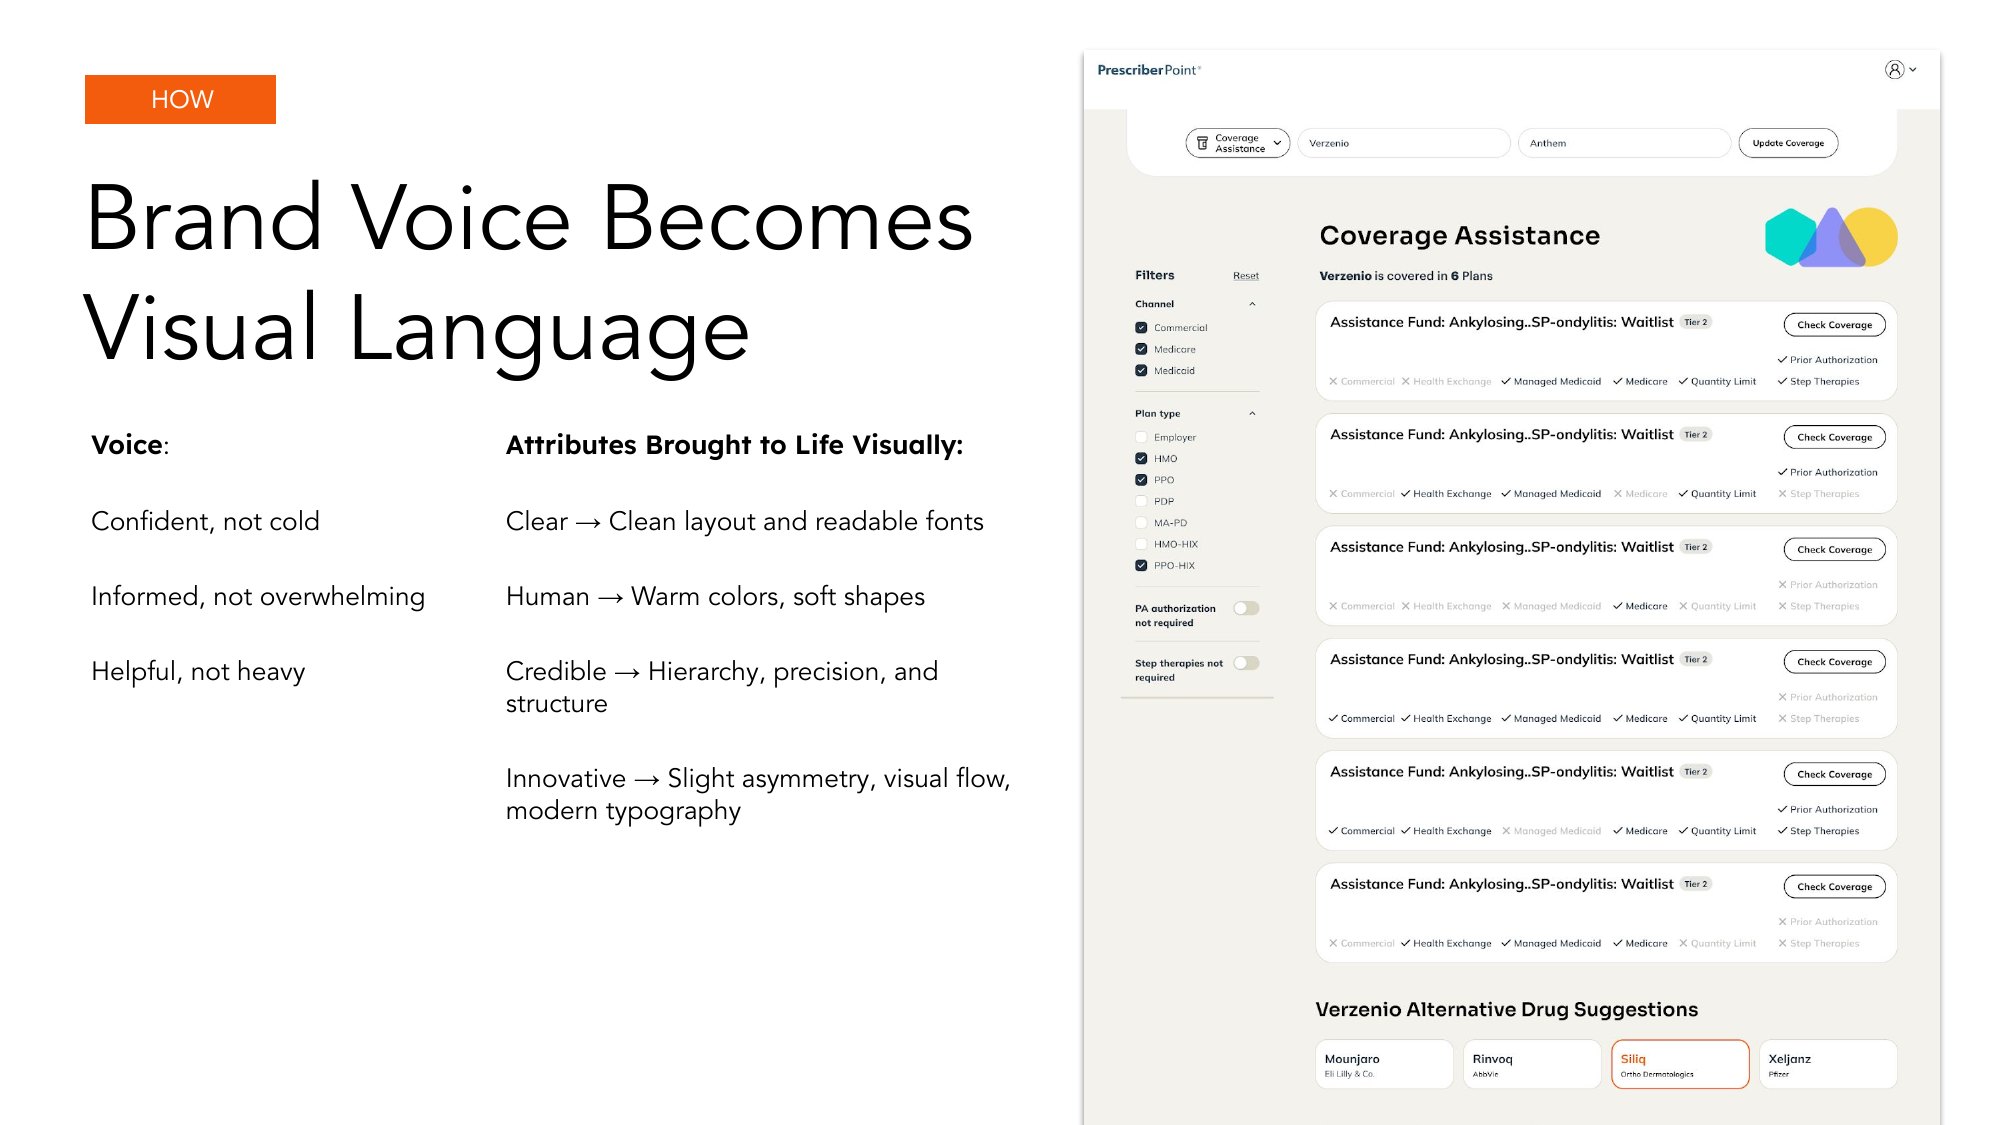
The brand concept that came out of it was Reimagining Access: not only access to medications, but to the clarity, trust, and support needed to navigate them. I translated it into design direction for Marketplace: simplicity in what’s shown, warmth in how it’s shown, and a calm, modern visual system that signals credibility without feeling clinical. It became a new visual language across the entire site, and we redesigned a number of pages to match it.




Design the path from visitor to customer
Before redesigning the homepage, I defined its role in the business. OneHub’s growth plan relied on clinic staff signing up and switching on their own. My research, and how clinics work, said otherwise: staff don’t change the tools they use for prior authorization without their managers, IT, and procurement, and moving off an established platform can take six months to a year.
So I framed Marketplace as the pipeline to that decision, in four tiers, each with a reason to move up to the next. The homepage would be the front door to the first.
Signs up whenThey find something worth coming back to
Gets personal whenEach visit learns more about their role, clinic, and medications
Return visits build trust
Leads to the platform whenStaff champion it to their managers
Decided byThe clinic, not one user
I then mapped every entry point into the tiers. Each job on the homepage, plus drug pages and pharma campaign pages, was its own entry point at Tier 1, open to anyone arriving from search, an AI answer, or a campaign. Each led one step deeper in exchange for an account: richer detail on a comparison, a coverage requirement, or a savings program. Account creation flexed with the entry point, from a light sign-in to full onboarding, and campaign pages converted to a demo request instead.
Two paths led to OneHub. From the homepage, a signed-in home brought back the same jobs, personalized to a person’s role, clinic, and medications. From prior authorization, a lighter version of OneHub let staff start with one task before their clinic took on the full platform, end to end. I set one rule for the map: the five jobs on the public homepage had to appear, personalized, in Tiers 3 and 4, so signed-in users kept the tools that brought them in.
Redesign the homepage around jobs to be done
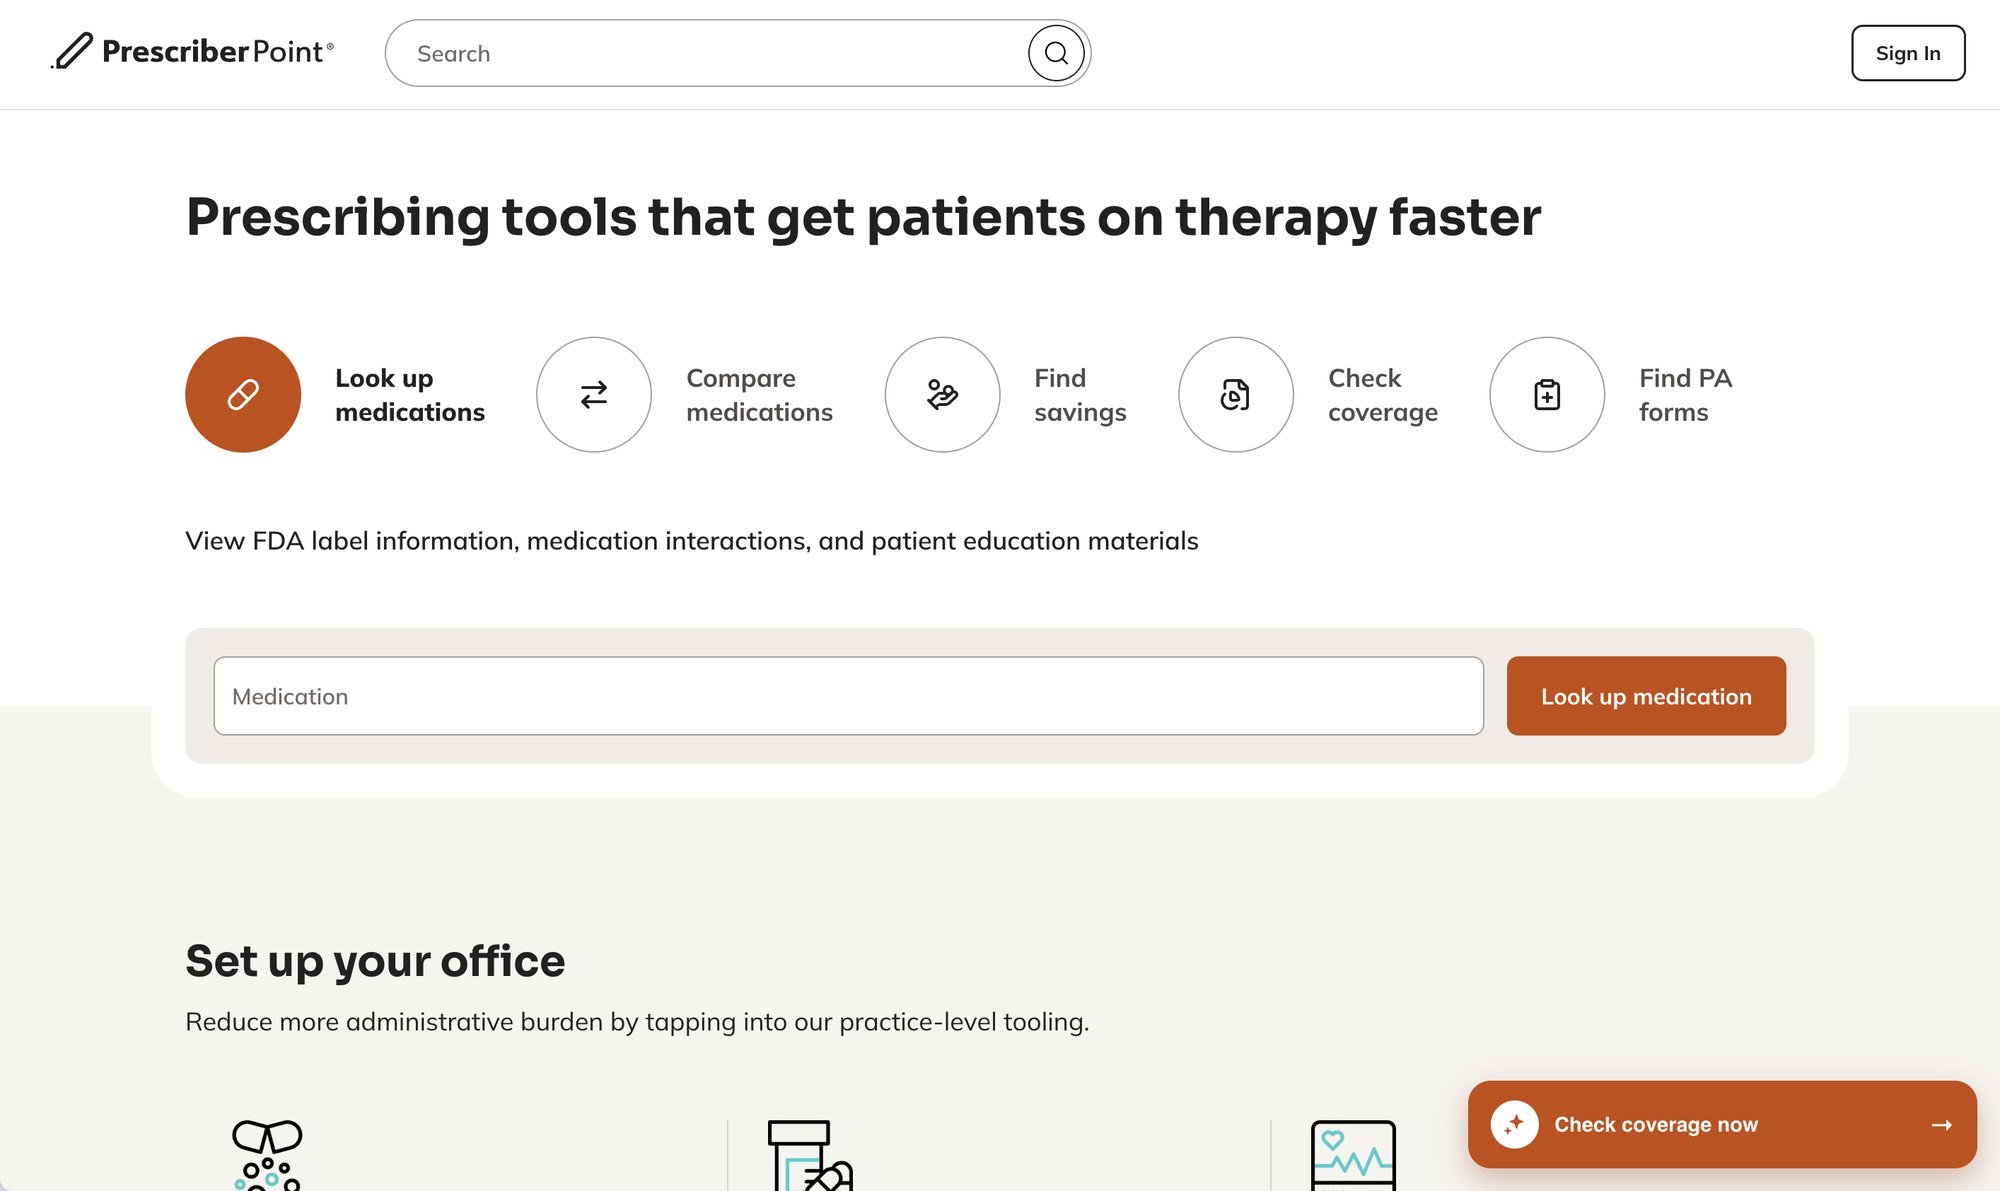
The homepage became the center of the redesign and the front door to the first tier. My goal was for it to work as the first page of the product rather than a marketing page: a visitor should be able to complete a task from it before reading anything about the company.
That led to five decisions:
- Lead with the jobs people already search for. The top of the page worked the way Kayak does for travel: pick the job, enter what you know, and go. Look up a medication, compare two that do similar things, find savings programs, check coverage under a particular insurer, or find prior authorization forms.
- Keep marketing out of the way. No role prompts or promotional claims between a visitor and the task they came for.
- Serve two audiences on one page. Every module had a primary user doing a job, and also read as credible to the people evaluating the platform, from clinic directors to partners.
- Leave room to flex. A row for platform offerings like samples and OneHub could hold one, two, or three modules, so priorities could shift without a redesign.
- Organize coverage by therapeutic area. That matched how prescribers think about medications, and showed the breadth of the catalog at a glance.
It launched with the rebrand on September 5, 2025.
Workflow tools
Utilities people use every day, which bring them back.
- Includes
- Medication comparison, prior authorization, savings, coverage by therapeutic area
- Moves
- Return visits, tool use, accounts
- For
- Clinic staff, prescribers
Next steps
Modules that open a deeper relationship with the platform.
- Includes
- Samples, OneHub, medication updates
- Moves
- Click-through, demo requests
- For
- Prescribers, clinic directors
Trust infrastructure
Choices that don’t shout, but make the tools feel reliable.
- Includes
- Module priority, role-aware design, plain language, breadth of coverage
- Moves
- Return usage, credibility
- For
- Clinic staff, clinic directors
Perception infrastructure
Signals of maturity for anyone assessing the platform.
- Includes
- Design system polish, trust points, depth of therapeutic coverage
- Moves
- Confidence, low bounce
- For
- Clinic leaders and partners
Define OneHub through a context scenario
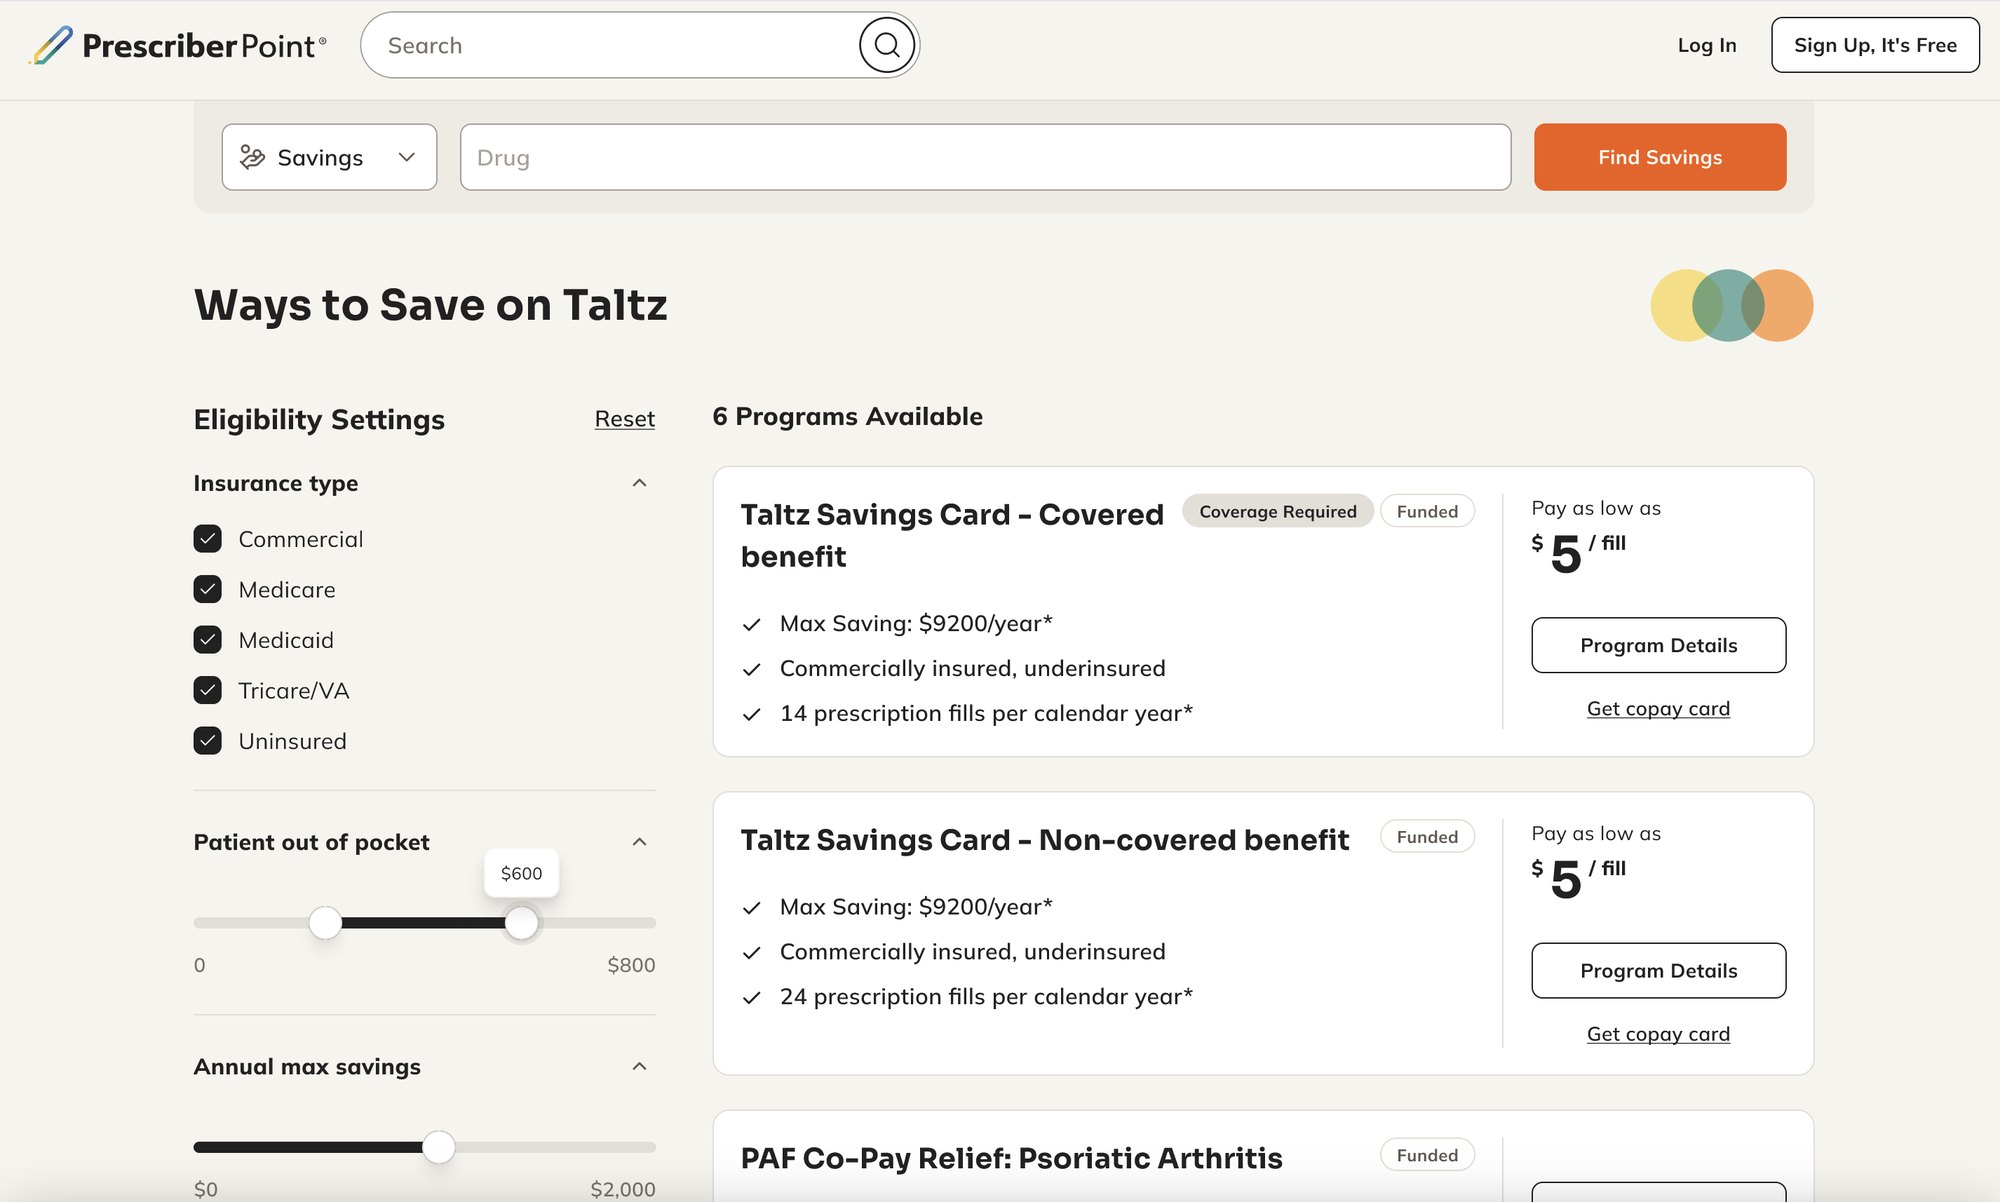
I wrote the original context scenario for OneHub in May 2024. Following Goal-Directed Design, it describes how people are supported, without screens or technology. In it, the system identifies the need for prior authorization before anyone has to discover it.
- Prescriber
Dr. Smith chooses Taltz for Mary’s plaque psoriasis. The clinical and prescription context reaches PrescriberPoint through the electronic health record.
- PrescriberPoint
Mary’s insurer requires a systemic therapy first. The flag appears while Dr. Smith is still in the record, with methotrexate as the step-therapy option, and he chooses it.
- Prescriber
He reviews a prescription already filled in with dose, quantity, and refills, and sends it.
- Medical assistant
Janice reviews the prior authorization PrescriberPoint prepared, corrects what needs correcting, and submits it. No one chases a signature.
- Patient
Mary leaves knowing what happens next, instead of coordinating between the clinic, insurer, and pharmacy herself.
- Patient
She checks her status in a tracker, and finds financial assistance for her new medication.
- PrescriberPoint
The approval arrives, and the prescription goes to the pharmacy without anyone checking for it.
Each person kept the decisions that needed their judgment: Dr. Smith made the clinical calls, Janice reviewed what was submitted, and Mary could check her status. The system handled the handoffs between them.
The scenario set OneHub’s interaction model. It took engineering about a year to build the agentic services behind it. I put one of my designers on OneHub to flesh out the experience with the product and engineering team, and consulted from the outside.
Track two
Leading the practice
An in-house team, a shared way of working, and principles for generative AI.
Build an in-house practice
I staffed the team to match the work. Researchers covered both products, a content designer made complex medical and insurance language clear, and two product designers worked across Marketplace and OneHub. I set up a model for how leadership, product discovery, and product delivery fed each other, so the team knew where research and design entered a decision, and where they handed off.
We also formalized the design system, with descriptions and annotations detailed enough for AI tools to read and use.
Set the terms for working with AI
I joined just as generative AI was taking off, and there was pressure to use it everywhere before anyone knew where it helped. My team tested the AI design and prototyping tools as they appeared, and I built small tools of my own, like one that helped people judge whether a research task suited AI, a person, or both.
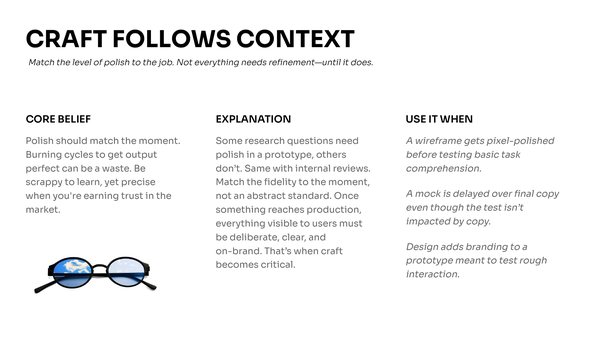
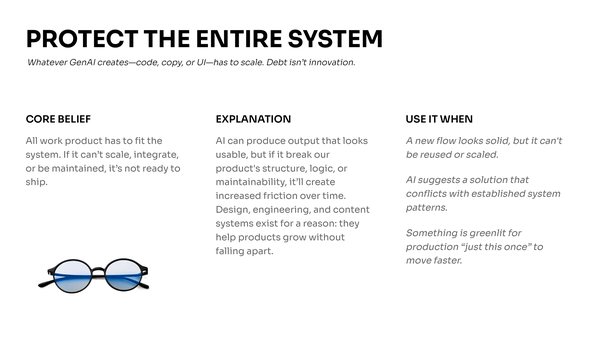
To give teams a shared approach, I wrote a deck of six operating principles for using generative AI in product development. Its premise: generative AI makes even weak input sound authoritative, so teams have to be clear about their goals before they use it. Each principle names a core belief, explains it, and lists the moments to use it.




What happened
The first tier of the pipeline shipped with the redesign, and the homepage paths brought people in, mostly through search. Instead of building the next tiers, the company invested in an identity graph, to infer who was visiting from data about them. Visitors still had no reason to create an account or come back on their own.
As interim product lead for Marketplace, I made the case for owned audience to leadership in late 2025: build the second and third tiers, so prescribers and clinic staff would sign in, identifying themselves, because the platform helped them with their work. I argued that people who return on their own would lower the cost of every campaign and shorten the path to OneHub. My team began work on it. I left in early 2026, before the company acted on it.
In their words
“Sean put processes in place to create a bridge between marketing & product that fostered continuous collaboration that set me and my team up for success from my Day 1. […] On larger cross-functional initiatives, Sean was paramount in validating the business need for defining a core brand identity and securing premium partners to facilitate deliberate phased planning, which set the organization up for success in the short term for launch in September ‘25. Concurrent to that initiative, Sean facilitated formalizing of our Design System internally to ensure we had the components, artifacts and overall structure in place to be scalable in the long-term post-launch. […] I would highly recommend Sean to any organization seeking a department head or VP/SVP in Product design/UXR.”
“I had the opportunity to work closely with Sean at PrescriberPoint, where we partnered to take a product from 0 → 1. Sean’s user-centric design leadership and steady thoughtfulness were pivotal in helping us cut through early ambiguity and move out of the fuzzy front end. He has a rare ability to bring teams together and stay relentlessly focused on driving real user value.”
“Sean deeply understands the value of building for real users and was consistently the strongest advocate for research. He has an exceptional instinct for knowing when to invest deeply in discovery and when it’s appropriate to take informed risks, which creates momentum without sacrificing quality.”
Key learnings
- The customer who pays isn’t the user who does the work.Manufacturers paid for prescriptions filled and saw prescribers as the way to get them. The research showed the work happening one step later, with clinic staff. When a business has more than one customer, design should start by finding who does the work that creates value, and build for them.
- Search traffic isn’t an audience.Search can bring people to a page once, but it doesn’t bring them back. Accounts, personalization, and tools that remember a person’s work are what make people return, and returning users make every other part of the business cheaper to run.
- Workflow tools are adopted by organizations, not individuals.A clinic doesn’t change how it handles prior authorization because one staff member signed up. Products that replace established tools have to win the people who use them and the people who approve them, and that takes time. Planning for it belongs in the product strategy.
- AI makes unclear goals more costly.Generative AI produces convincing output from vague input, and it lets individuals move faster than their teams can stay aligned. The principles I wrote were less about tools than about agreeing on goals, coordinating, and reviewing output before acting on it.
- Choose where to spend your influence.I came in to lead design and research, and I kept taking on larger questions: how clinics adopt software, what would bring people back, and what the business model required. Those questions were worth raising. But I pushed hardest where leadership was least interested, and spent credibility on arguments the company wasn’t ready to act on, at a cost to me and to my team. I still make the case when the stakes call for it. Now I first find out where decisions are made and who wants help making them, and pick when to push.
Questions about this project? Email me.